
Upper Extremity Nerve Injuries: High-Yield Guide to Axillary, Radial, Median, and Ulnar Nerve Lesions
Learn the most tested upper extremity nerve injuries fast: axillary, radial, median, and ulnar nerve lesions, fracture associations, sensory findings, and…
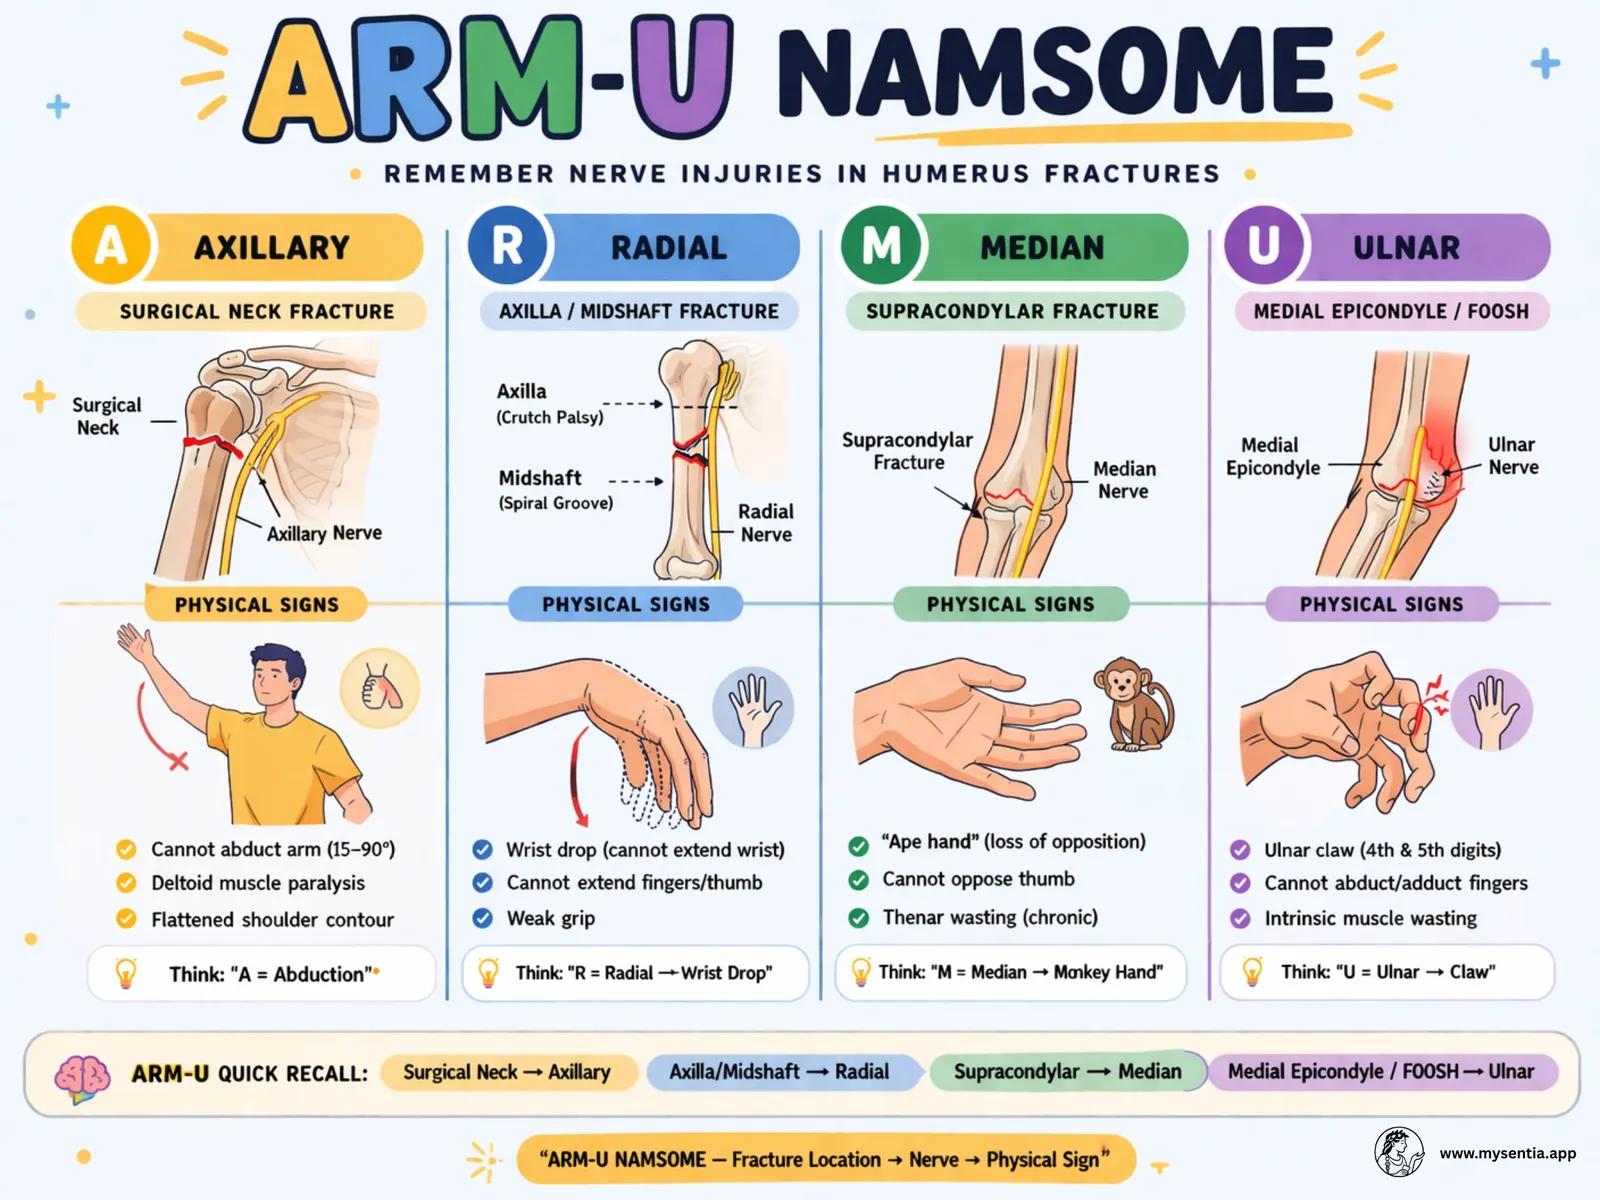
Upper extremity nerve injuries are one of the most exam-tested and clinically relevant anatomy topics in medicine because they connect trauma, orthopedics, neurology, and bedside physical exam. The core task is simple: localize the lesion from the motor deficit, sensory loss, and mechanism of injury. Most exam questions revolve around four nerves: axillary, radial, median, and ulnar. Common presentations include shoulder abduction weakness after proximal humerus fracture or dislocation, wrist drop after humeral shaft injury, thenar weakness in carpal tunnel syndrome, and clawing with interosseous weakness in ulnar neuropathy. Upper extremity nerve injury evaluation should always include a careful neurovascular exam because associated arterial injuries can accompany key fracture patterns.
Why upper extremity nerve injuries matter
In the upper limb, peripheral nerves are long, relatively superficial, and vulnerable to trauma, compression, fracture displacement, entrapment, and iatrogenic injury. Clinically, these injuries may present with pain, paresthesias, weakness, sensory loss, or a classic deformity. On exams, the highest-yield questions usually test one of three things: which nerve is injured, where along the nerve it is injured, or what structure is at risk with the same mechanism.
The fastest way to localize an upper extremity nerve injury
Think in this order:
1. What movement is lost?
- If the patient cannot abduct the arm from 15 to 90 degrees, think axillary nerve.
- If the patient has wrist drop, think radial nerve.
- If thumb opposition is weak, think median nerve.
- If finger abduction and adduction are weak, think ulnar nerve.
2. Where is the sensory loss?
- Lateral shoulder points to the axillary nerve.
- The dorsal first web space is the classic autonomous zone for the radial nerve.
- The palmar tip of the index finger is a strong median nerve test point.
- The little finger is the classic ulnar sensory clue.
3. What was the mechanism?
- Surgical neck fracture or anterior shoulder dislocation suggests axillary nerve injury.
- Midshaft humerus fracture suggests radial nerve injury.
- Supracondylar fracture suggests median nerve injury and raises concern for the brachial artery.
- Medial epicondyle or cubital tunnel problems suggest ulnar nerve injury.
Axillary nerve injury
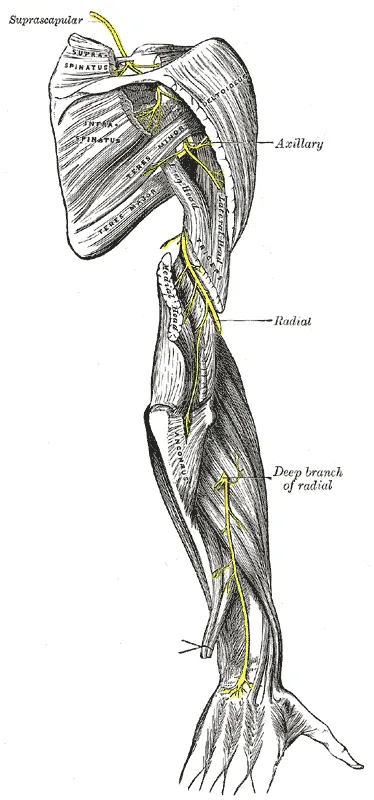
The axillary nerve arises from the posterior cord, mainly C5-C6, passes through the quadrangular space, and travels with the posterior circumflex humeral artery. It innervates the deltoid and teres minor, and its key sensory branch supplies the lateral shoulder, often described as the regimental badge area. The most tested mechanisms are surgical neck fractures and anterior shoulder dislocations.
The classic presentation is a patient who can weakly initiate abduction with supraspinatus but cannot properly abduct from 15 to 90 degrees because the deltoid is weak. Sensory loss over the lateral shoulder is the matching clue. Mild weakness of external rotation can also appear because teres minor is axillary-innervated.
Most axillary nerve injuries after dislocation are neuropraxias and often improve with conservative management, though persistent or severe deficits may need further evaluation.
High-yield pearl:
If the question gives a proximal humerus fracture + inability to abduct beyond 15 degrees + lateral shoulder numbness, the answer is almost always axillary nerve.
Radial nerve injury
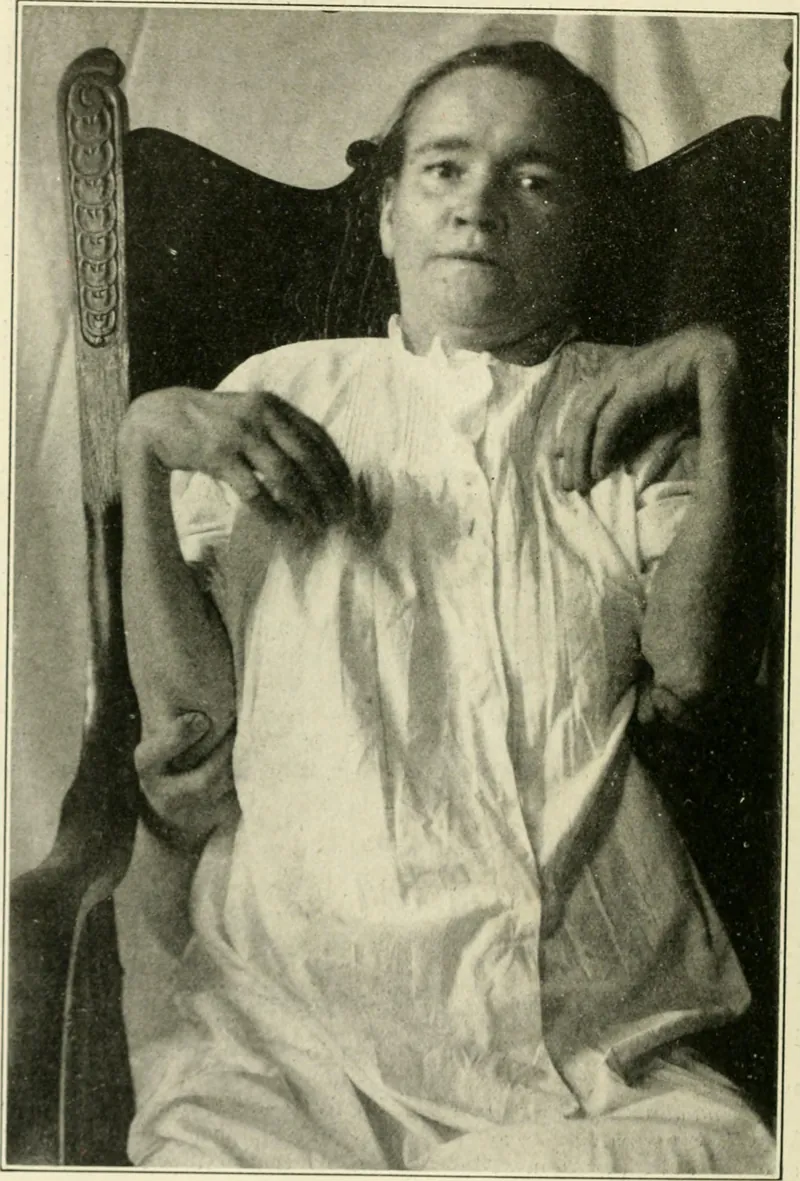
The radial nerve comes from the posterior cord, C5-T1, and courses in the spiral groove with the profunda brachii artery. It is the major nerve of extension in the upper limb. Its hallmark deficit is wrist drop, usually with weakness of finger extension as well.
A high radial lesion at the axilla, as in crutch palsy, can weaken elbow extension, wrist extension, and finger extension, with broader sensory loss. A spiral groove lesion, classically from a midshaft humerus fracture or compression during sleep, usually causes wrist drop while sparing most triceps function. A posterior interosseous nerve lesion causes finger and thumb extension weakness with no sensory deficit because PIN is a motor branch. A superficial radial nerve lesion causes sensory symptoms only.
Radial nerve palsy is a well-known complication of humeral shaft fractures. A StatPearls review reports radial nerve palsy in about 11.8% of humeral shaft fractures, and many closed-fracture palsies recover spontaneously. Recovery is often observed over time rather than treated with immediate exploration in uncomplicated closed injuries.
High-yield pearl:
If the stem says midshaft humerus fracture + wrist drop + preserved elbow extension, localize the lesion to the radial nerve in the spiral groove.
Median nerve injury
The median nerve is formed by contributions from the lateral and medial cords and typically carries fibers from C5-T1. It travels with the brachial artery in the arm and then passes between the heads of pronator teres before entering the forearm. At the wrist, it passes through the carpal tunnel.
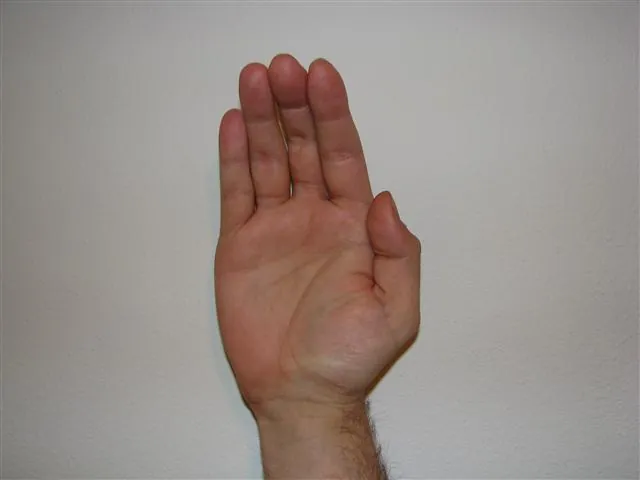
Median nerve injury classically affects thumb opposition, thenar muscles, and sensation to the lateral palm and lateral 3.5 digits. A proximal lesion can also weaken pronation, wrist flexion, and flexion of the thumb IP joint and index DIP joint via the anterior interosseous nerve distribution. AIN palsy is especially high yield because it is motor only and produces an abnormal OK sign.
The most tested median neuropathy is carpal tunnel syndrome, which usually causes nocturnal paresthesias in the thumb, index, middle, and radial half of the ring finger. The palmar cutaneous branch arises proximal to the tunnel, so sensation over the central palm is often preserved. Thenar weakness or atrophy suggests more advanced disease.
High-yield pearl:
If the patient has night symptoms, thenar weakness, and preserved central palm sensation, think median nerve compression in the carpal tunnel.

Ulnar nerve injury
The ulnar nerve arises from the medial cord, typically C8-T1, passes posterior to the medial epicondyle, and enters the forearm through the cubital tunnel region. At the wrist, it travels through Guyon canal. It supplies the interossei, the adductor pollicis, the medial lumbricals, and in the forearm it innervates flexor carpi ulnaris and the medial half of flexor digitorum profundus.
Its signature deficits are weakness of finger abduction and adduction, weak grip, sensory loss in the little finger and ulnar half of the ring finger, and clawing of digits 4 and 5. Froment sign points to weakness of the adductor pollicis.
The two classic entrapment sites are the cubital tunnel at the elbow and Guyon canal at the wrist. Elbow lesions are more likely to affect FCU, medial FDP, and dorsal ulnar sensation. Wrist lesions spare those proximal branches and can produce the classic “ulnar paradox,” in which clawing appears worse distally because the FDP remains intact.
High-yield pearl:
If the patient has clawing of the 4th and 5th digits + loss of finger abduction, think ulnar nerve first.
The fracture-to-nerve map every med student should know
The most testable trauma pairings are:
- Surgical neck of humerus → axillary nerve
- Midshaft humerus → radial nerve
- Supracondylar humerus fracture → median nerve and possible brachial artery
- Medial epicondyle / cubital tunnel region → ulnar nerve
If you memorize only one trauma map for upper extremity nerve injuries, memorize that one.
Branch lesions that create exam traps
This topic becomes hard when the lesion is in a branch, not the main nerve.
A posterior interosseous nerve lesion causes finger extension weakness without sensory loss. A superficial radial nerve lesion causes sensory loss without motor weakness. An anterior interosseous nerve lesion causes an abnormal OK sign without sensory loss. A deep branch of the ulnar nerve lesion in Guyon canal can cause intrinsic hand weakness with little or no sensory deficit depending on the exact zone.
These are classic NBME traps because the stem may give you a “radial” or “median” pattern but remove the sensory findings to force you to choose the branch lesion instead.
Management pearls
Not every nerve injury needs immediate surgery. Many upper extremity neuropraxias improve with conservative care, splinting, activity modification, and serial examination. In particular, radial nerve palsy in closed humeral shaft fractures is often managed expectantly because spontaneous recovery is common. Open fractures, vascular compromise, penetrating trauma, or persistent severe deficits increase concern for exploration.
For compressive neuropathies, first-line treatment is usually conservative unless there is significant weakness, atrophy, or refractory symptoms. Carpal tunnel syndrome often starts with splinting and activity modification, whereas progressive thenar weakness can prompt surgical decompression. Cubital tunnel management similarly begins conservatively in many patients before operative treatment is considered for severe or progressive cases.
One-minute exam approach
When given an upper extremity nerve injury stem, ask:
- What movement is lost?
- What sensory territory is affected?
- What was the mechanism: fracture, dislocation, compression, or entrapment?
- Is the lesion proximal, distal, or branch-specific?
- Is there a paired artery or fracture pattern I should recognize?
High-yield summary
Upper extremity nerve injuries are easiest when you reduce them to signature patterns. Axillary nerve injury causes lateral shoulder numbness and loss of abduction after surgical neck fracture or anterior dislocation. Radial nerve injury causes wrist drop, especially after humeral shaft injury or compression in the spiral groove. Median nerve injury causes thenar weakness, opposition loss, and classic carpal tunnel symptoms, while AIN palsy causes a motor-only OK sign deficit. Ulnar nerve injury causes clawing of digits 4 and 5, interosseous weakness, and sensory changes in the little finger, usually from cubital tunnel or Guyon canal pathology. If you can match the movement, sensory zone, and mechanism, most exam questions become straightforward.


